What Is Endocarditis? Symptoms, Causes, Risk Factors & Treatment

Medically Reviewed and Updated by Dr. Rae Osborn, Ph.D. - October 15, 2026
Edited by Abinaya Muralidharan, M. Pharm - October 15, 2026
Key Takeaways
- Endocarditis refers to inflammation affecting the inner lining of the heart and its valves. It may be infective or non-infective.
- Infective endocarditis is not contagious and usually develops when microbes enter the bloodstream and reach the heart.
- Symptoms vary and may include fever, fatigue, shortness of breath, heart murmur, night sweats, swelling, and skin changes.
- Risk is higher with certain heart conditions, artificial valves, previous endocarditis, poor oral health, weakened immunity, and injection drug use.
- Diagnosis may involve blood cultures, echocardiography, clinical assessment, and additional imaging when needed.
- Treatment depends on the type and cause and may include antibiotics, antifungals, anticoagulants, or surgery in some cases.
What Is Endocarditis?
Endocarditis is inflammation of the endocardium, which is composed of specialized endothelial cells that line the inside of the heart and form the surface lining of the heart valves.
There are two forms of endocarditis: infective and non-infective. Infective endocarditis is not contagious and is relatively uncommon. In 2021, its global age-standardized prevalence rate was 5.3 per 100,000 people. Globally, prevalence increased by 40.1% between 2010 and 2021. Non-infective endocarditis is the rarer of the two forms.
Endocarditis affects the inner lining of the heart and its valves, while other inflammatory or infectious conditions can affect different parts of the heart, such as the heart muscle.
Types of Endocarditis
Infective Endocarditis (IE)
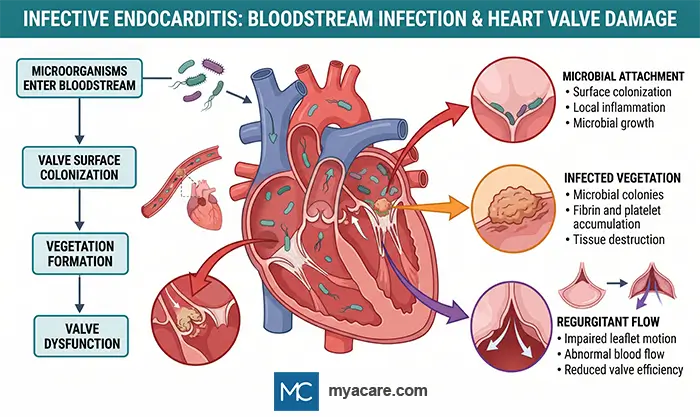
Infective endocarditis is usually a bacterial infection of the lining and, most often, the valves of the heart. The valves themselves are part of this inner connective tissue lining. IE leads to the formation of deposits (vegetations) on the surfaces of the valves. This leads to valve damage and potentially embolization, resulting in symptoms and possibly complications.
IE can be further classified into acute and subacute endocarditis. The acute type can be distinguished from the subacute type by how quickly the person becomes ill and how severe the symptoms are.
Factors affecting the severity of IE
Acute vs. subacute:
Acute endocarditis develops rapidly, typically over days, whereas subacute endocarditis progresses more gradually over weeks to months. Patients with subacute endocarditis generally do not have a high fever and tend to be less severely ill than those with acute endocarditis. IE can be fatal, with short-term mortality reaching 17% in some cases. However, treatment options are available.
Prosthetic valve vs. native valve:
These have different severities. Those with an infected prosthetic valve have higher morbidity and make up 20% to 30% of IE cases compared with patients where infection is on their own valves.
Location:
IE can also be classified by location – right- or left-sided valve or both (bilateral) – which affects its severity. Left-sided IE affects the mitral or aortic valves, which are on the left side of the heart. Similarly, right-sided IE affects the pulmonary and tricuspid valves on the right side of the heart. Bilateral IE impacts valves on both sides of the heart.
Infective endocarditis can result in vegetations on the heart valve; masses consisting of platelets, microbes, and fibrin. These can be seen on imaging using three-dimensional transoesophageal echocardiography, appearing as a softer texture than surrounding structures.
Non-Infective Endocarditis
In non-infective endocarditis, vegetations form on the valves, but they are sterile and do not contain pathogenic microbes. They consist of platelets and fibrin clots. This is known as nonbacterial thrombotic endocarditis (NBTE).
Other types of non-infective endocarditis
Libman-Sacks endocarditis:
This is a type of nonbacterial thrombotic endocarditis, also known as verrucous endocarditis. Libman-Sacks endocarditis affecting the left-sided heart valves (mitral/aortic) can occur as a complication of lupus.
Marantic endocarditis:
This type is associated with malignancy or other hypercoagulable states.
Causes of Endocarditis
What Causes Infective Endocarditis?
The causative organisms of IE are the following:
- Fungi: The fungus Candida albicans is commonly found causing thrush, and while it is not a common cause of endocarditis, it can occur in immunocompromised patients.
- Viruses: There have been some cases of infective endocarditis in patients with COVID-19. However, current evidence does not establish that COVID-19 directly causes infective endocarditis.
- Bacteria: Viridans-group Streptococcus and Staphylococcus aureus can infect the heart valves. Staphylococcus is the most common cause of endocarditis. Enterococcus is another pathogen linked to IE. HACEK organisms, including Haemophilus, Aggregatibacter, Cardiobacterium, Eikenella, and Kingella, and gram-negative bacteria can also cause bacterial endocarditis. Additionally, toxic shock syndrome, as a rare secondary bacterial complication following the flu virus, can also lead to infective endocarditis.
How bacteria can enter the body and cause IE
Dental procedures: Bacteria can spread from the gums and teeth during dental procedures, including extractions, implants, and periodontal surgery.
Skin infections and wounds: These, including burn injuries, can cause S. aureus bacteria to enter the bloodstream. Bloodstream infections (bacteremia) can produce endocarditis.
Procedures and infections of the gastrointestinal and genitourinary systems: These can possibly introduce pathogens that enter the blood and move to the valves.
Medical procedures: Invasive procedures, including the placement of intravenous catheters or implanted medical devices, like pacemakers or ICDs, can be a causative factor.
Other rare causes
Postpartum: A rare cause of endocarditis is postpartum infective endocarditis with Enterococcus faecalis after delivery.
UTI: Although uncommon, a UTI can cause infective endocarditis through the bacterium Proteus mirabilis.
Contact lens: Bacterial endocarditis can, on rare occasions, be caused by incorrect contact lens usage.
What Causes Non-Infective Endocarditis?
The causes of non-infective endocarditis include the following:
- Vasculitis: An inflammatory response of the blood vessels.
- Immune complexes: These occur when an antigen and an antibody are bound together. While such binding is a normal response of the immune system, research shows that they can be related to endocarditis. Immune complexes have also been seen in some patients with COVID-19.
- Hypercoagulation: In this situation, blood clotting happens too readily, resulting in a buildup of clots on valve tissue.
- Systemic lupus erythematosus: Commonly called lupus, this is an autoimmune disease.
- Behçet disease: This is an uncommon blood vessel disease that can impact the valves.
- Hypereosinophilic syndrome: A condition where there are too many eosinophils, which cause organ damage and result in Löffler endocarditis.
- Flu: While it is not a direct cause of the condition, there has been a reported case of nonbacterial thrombotic endocarditis that occurred due to hypercoagulation caused by acute respiratory distress syndrome (ARDS) associated with the influenza virus.
What Are the Symptoms of Endocarditis?
The signs of endocarditis are not always obvious and can also indicate a different condition, making diagnosis challenging. Symptoms can overlap and vary depending on whether the endocarditis is due to infection or not.
Infective Endocarditis Symptoms
Symptoms of endocarditis that are subacute bacterial or acute bacterial include the following:
Systemic symptoms:
- Night sweats
- High-grade fever of 39oC for acute IE, which has rapid onset and is severe. A low-grade fever is seen in subacute IE, where onset is gradual, over weeks, and the illness is not as severe.
- Chills
- Poor appetite
- Flu-like symptoms
- Weight loss
- Fatigue and joint pain
- Headache
Heart-related symptoms:
- Sore chest when breathing
- Shortness of breath
- Heart murmur
- Edema (swelling) in the legs or abdomen
Skin:
- Janeway lesions - spots on the hands and feet
- Osler's nodes - bumps on the fingers and toes
- Petechiae - tiny spots on the skin
- Skin rashes and unexplained skin changes
Nails:
Splinter hemorrhages are an endocarditis symptom seen in the fingernails
Eye:
Roth spots (retinal hemorrhages with white or pale center)
Kidney:
Blood in urine (hematuria)
Non-Infective Endocarditis Symptoms
- Fever
- Shortness of breath
- Heart murmur: Indicating abnormal heart valve function
- Heart palpitations: Fluttering or feeling of a rapid heartbeat
- Valvular regurgitation: In this case, the valves do not close properly, leading to blood leaking backward during heart muscle contractions.
Endocarditis Complications
Endocarditis is a serious condition that affects the heart and may also impact other organs.
Complications of Infective Endocarditis
Infective endocarditis can also lead to serious complications that may cause organ failure and, in severe cases, fatality.
- Valve regurgitation and heart failure: Heart failure is the most common complication of IE. Heart valve damage can cause regurgitation and may lead to heart failure.
- Inflammation of the aorta: Infection can spread to the aortic wall and cause inflammation (aortitis).
- Atrial fibrillation: IE can be associated with atrial fibrillation, an irregular heart rhythm.
- Heart block and other conduction abnormalities: Infection extending around the valve can affect the heart’s electrical conduction system and cause heart block or other conduction abnormalities.
- Abscess of the myocardium, the muscle layer of the heart: IE can extend into the surrounding heart muscle and cause an abscess.
- Aortic root abscesses, pseudoaneurysms, and fistulas if the infection spreads.
- Infected material that spreads throughout the body: Pieces of infected material can break away and spread through the bloodstream as septic emboli, affecting distant organs.
- Blood clots in the lungs, spleen, or brain: This can also lead to stroke.
- Glomerulonephritis: A type of kidney inflammation that can result from IE. It is most often due to an immune response to bacteria in the blood. This causes injury to the kidney. Methicillin-resistant Staphylococcus aureus (MRSA) and Streptococcus viridans have been implicated in these cases.
- Infections: Infective endocarditis complications also include infections, such as brain abscesses, in the central nervous system.
Complications of Non-Infective Endocarditis
Non-infective endocarditis often leads to complications such as embolization, where blood clots travel through the blood vessels and become deposited in vessels or other organs. Some of the consequences of emboli can include:
- Heart attack
- Stroke
- Pulmonary embolus
Risk Factors for Endocarditis
Certain people are at a higher risk for endocarditis, as given below.
- People who use drugs intravenously; contaminated needles can inadvertently introduce bacteria into their bloodstream. There has been a rise in endocarditis linked to injection drugs, with 33.7% of surgeries to fix damaged valves attributed to endocarditis from drug use. Intravenous drug use was responsible for 15.3% of IE cases in 2010, which increased to 29.1% in 2015.
IE cases among people with substance use disorders sharply increased when COVID-19 began, with the biggest increases between 2021 and 2022. This is partly attributed to pandemic-era disruptions to addiction care. For management, hospitals are increasingly pairing cardiac treatment with addiction care.
- Immunocompromised individuals, such as people with cancer, cannot easily fight off infections, making them vulnerable to infective endocarditis.
- People with cardiovascular problems, such as heart valve disorders, calcification of the valves, or congenital heart defects like mitral valve prolapse.
- Individuals who have an artificial heart valve are at risk. A valve can be replaced by open- heart surgery or by transcatheter aortic valve implantation (TAVR).
TAVR is a procedure in which an artificial valve is placed in the heart by a less invasive procedure using a catheter. This avoids the more invasive open-heart surgery. TAVR-associated endocarditis can occur, but the chance of IE from TAVR is low. However, patients who are infected do poorly.
Not every valve condition will result in IE. The risk depends on the underlying cardiac condition and degree of exposure to microbes.
- Other cardiac factors that can increase the risk for IE include previous valve surgery, previous episode of endocarditis, rheumatic heart disease, congenital heart disease, and a heart transplant with valve disease.
- Poor oral health can increase the risk of IE, as can recurrent or persistent skin infections.
- Age is a factor, with older adults having a higher incidence of IE because of underlying health conditions.
How Is Endocarditis Diagnosed?
The diagnosis of endocarditis can be challenging because early signs can be vague.
However, prompt diagnosis is important because complications can be serious or even fatal. Diagnostic measures can also determine whether the illness is infective or non-infective, which helps plan the most appropriate treatment measures. A doctor will review the patient's medical history and run tests. The tests include:
-
Blood Tests
This includes a complete blood cell count and clotting time determination. White blood cells and immunoglobulin complexes may increase, but these are not specific to endocarditis.
-
Blood Cultures
Blood cultures can help identify bacteria or other pathogens in the bloodstream that may be associated with infective endocarditis. However, a negative blood culture does not necessarily rule out infective endocarditis. In culture-negative endocarditis, the infection may still be present even though the causative organism is not detected by the test.
-
Echocardiography
This is a type of ultrasound that visualizes the heart to show whether there are any valvular or other structural abnormalities.
Echocardiography plays an important role in diagnosing infective endocarditis (IE) and forms part of the 2023 Duke-ISCVID diagnostic criteria. Findings that may support IE include vegetations, valvular or leaflet perforation or aneurysm, abscesses, pseudoaneurysms, intracardiac fistulas, significant new valvular regurgitation, and new partial separation of a prosthetic valve.
While an echocardiogram is the first choice of imaging to diagnose IE, a normal echocardiogram does not completely rule out IE. This is especially the case with prosthetic valves, cardiac devices, or small vegetations. In these situations, transoesophageal echocardiography (TEE/TOE) and sometimes CT or other imaging may be needed.
-
Clinical Exam
If patients have symptoms of endocarditis along with findings from the tests mentioned above, particularly blood cultures and echocardiography, this may indicate the presence of endocarditis.
Additional tests may be needed to check for complications:
- ECG can be used to check for rhythm and conduction complications that happen when infection moves into the heart muscle and conduction tissue.
- Chest imaging can be used to check for heart failure and pulmonary involvement.
- CT can detect perivalvular/periprosthetic complications such as embolic lesions and abscesses.
- MRI of the brain could show neurologic complications.
- PET or CT can be used to test for prosthetic-valve or device cases.
- Urinalysis ties to hematuria or proteinuria indicating renal involvement due to IE.
No single blood test confirms endocarditis; diagnosis relies on the overall clinical picture, cultures, imaging, and formal criteria used together.
Differential Diagnosis
Endocarditis vs. Pericarditis
Pericarditis is inflammation of the sac lining the heart, while endocarditis affects the inner heart lining. Pericarditis is more commonly due to a virus or has no identifiable cause, while endocarditis is often linked to bacteria.
Endocarditis vs. Myocarditis
Myocarditis is inflammation of the heart muscle, rather than the inner lining and valves of the heart. It can be caused by infectious microbes as well as autoimmune diseases. Chest pain is one of the possible signs of myocarditis. Like endocarditis, myocarditis can also lead to heart failure.
Endocarditis vs. Rheumatic Fever
While endocarditis affects the heart valves, rheumatic fever is, initially, a systemic disease caused by Strep A bacteria. This infection can spread to the valves, causing rheumatic heart disease.
How Is Endocarditis Treated?
Treatment for non-infective endocarditis typically involves anticoagulant medications to help prevent blood clots. Survival rates for non-infective endocarditis are lower than those for infective endocarditis, as patients often have other serious underlying illnesses that can affect their ability to recover.
Infective Endocarditis
Potential sources of infection, such as catheters, should be identified and removed where appropriate. Dental health should also be evaluated to determine whether it may be a source of bacteria. For patients with certain heart valve defects, prophylactic antibiotics may be recommended before specific dental procedures to help reduce the risk of future infective endocarditis.
The following antibiotics are prescribed for infective endocarditis:
- Gentamycin
- Penicillin
- Ampicillin
- Vancomycin (for resistant Staphylococcus)
Infective endocarditis treatment entails antibiotic administration over several weeks. Treatment should be individualized. Antibiotic selection and its duration depend on the organism, culture results, valve type, drug allergies, kidney function, and local resistance patterns.
For fungal endocarditis, antifungals are used. Echinocandin or voriconazole is used depending on the fungal organism involved.
Endocarditis Indications for Surgery
Surgery may be needed if there is severe valve damage and regurgitation or if large vegetations are present on the valves. Heart failure and abscesses are also indications for endocarditis surgery. Another reason is persistent infection even after 5 or 7 days of antibiotic therapy. Open heart surgery is needed when there is prosthetic-valve infection and large embolization-prone vegetations.
Endocarditis surgery
During surgery, damaged or infected tissue is removed. The affected valves may be repaired or reconstructed; however, in severe cases, valve replacement may be necessary. If the causative microbe is unknown, tissue samples may be sent for testing.
Monitoring of endocarditis treatment includes repeat blood cultures, kidney monitoring for certain medicines, and assessment for embolic complications.
Prevention of Endocarditis
Routine dental and oral hygiene is important since a tooth infection, abscess, root canal, or cavities (dental caries) can cause endocarditis.
Antibiotic prophylaxis may be necessary during dental procedures for people with high-risk cardiac conditions. This includes patients with prosthetic valves or certain prosthetic materials and those who are immunocompromised (in select cases).
The 2021 AHA guidance reserves antibiotic prophylaxis for selected highest-risk patients, such as those with artificial heart valves, prior endocarditis, certain congenital heart conditions, cardiac transplant recipients with valve problems, and for specific dental procedures that involve the oral mucosa and gingiva.
Skin and wound care is important to prevent bacteremia, which could spread to the heart valves.
Avoiding intravenous drug use and needle sharing, which can introduce bacteria into the blood, is recommended for endocarditis prevention.
Infection-prevention practices should be in place for catheters and implanted cardiac devices.
Recovery and Outlook
Endocarditis can take several months to recover from, and fatigue is common during this time. Patients may have some physical deconditioning and mental and cognitive issues until fully recovered.
The cure rate for endocarditis is high when diagnosed early and treated quickly.
There is a 5% to 10% chance of recurrence if you have had endocarditis before. An unexplained fever may be a sign the condition has returned.
Life expectancy after infective endocarditis varies depending on age and other underlying health conditions. Among people who survive hospitalization, five-year survival is approximately 75% to 85%.
It is important for patients with endocarditis to complete the full antimicrobial course, keep follow-up appointments, and monitor for recurrent symptoms or long-term valve problems.
When to Seek Medical Attention
If you experience any of the symptoms below, seek medical care promptly, as early evaluation and treatment can help prevent complications such as heart valve damage, heart failure, stroke, or the spread of infection. Medical evaluation is recommended if you experience any of the symptoms listed below. While these symptoms can occur with other medical conditions, it is important to discuss them with a doctor, particularly if there is a concern that endocarditis may have returned.
- Pain or discomfort in the chest and an unusually rapid heartbeat (tachycardia)
- Feeling unusually tired or weak and having a fever above 100°F (38.4°C) and chills
- Excessive sweating at night
- Difficulty breathing or shortness of breath (dyspnea)
- Reduced appetite accompanied by weight loss
- Aching muscles and joints and skin rash
- Fluid buildup causing swelling in the legs or abdomen
- Blood in the urine (hematuria)
Conclusion
Endocarditis is a serious condition, with a mortality rate of about 25%. Timely diagnosis is vital to help guide appropriate treatment and reduce the risk of complications. Doctors also need to determine the type and cause of endocarditis so that treatment can be tailored accordingly.
Frequently Asked Questions
Can endocarditis happen without a heart condition?
Yes, 40% of patients without a pre-existing cardiac problem develop endocarditis.
Can endocarditis heal on its own?
No, endocarditis does not heal on its own and needs prompt treatment.
Can bacterial endocarditis be cured?
Yes, provided the person gets treatment as soon as possible.
Can you have endocarditis without a fever?
Yes. Although fever is a common symptom, endocarditis can occur sometimes with low-grade or no fever, specifically in people with subacute or chronic infection.
What can happen if endocarditis is left untreated, and how does it affect life expectancy?
Untreated endocarditis causes heart valve damage and heart failure. With acute endocarditis, the condition can be fatal in less than 6 weeks, and with subacute endocarditis, it can be fatal in under 6 months.
How long can you have endocarditis without knowing?
It depends on the type of endocarditis. You can have subacute endocarditis for several weeks without knowing it, and you can have noninfectious endocarditis without ever being aware since symptoms may be absent.
To search for the best Cardiology Healthcare Providers and Doctors in Germany, India, Indonesia, Malaysia, Spain, Thailand, the UAE, the UK and the USA, please use the Mya Care Search engine.
To search for the best doctors and healthcare providers worldwide, please use the Mya Care search engine.

Dr. Rae Osborn has a Ph.D. in Biology from the University of Texas at Arlington. She was a tenured Associate Professor of Biology at Northwestern State University, where she taught many courses to Pre-nursing and Pre-medical students. She has written extensively on medical conditions and healthy lifestyle topics, including nutrition. She is from South Africa but lived and taught in the United States for 18 years.

Abinaya Muralidharan holds an M. Pharm in Pharmacology. She specializes in turning complex science into clear, credible content, with experience spanning clinical safety, regulatory affairs, and medical communications. She has worked across various therapeutic areas, including but not limited to oncology, dermatology, hematology, and cardiology. She has authored publications in peer-reviewed journals, including original research papers and review articles.
References:
Featured Blogs

Medically Induced Coma: What It Is, How It Works & Recovery